The Conversation I Wasn’t Expecting
I walked into my annual physical in January knowing exactly what my doctor was going to say about my weight. I’d prepared myself. I’d seen the headlines. Ozempic, Wegovy, Zepbound — these drugs have become as common a topic at dinner parties as inflation and true crime podcasts. Everyone’s either taking them, considering them, or loudly declaring they never will. My doctor, I assumed, would follow the script: lose weight through diet and exercise, all the standard recommendations.

Instead, she asked me a question that caught me completely off guard: “Have you thought about medication?” Not casually. Not as an afterthought. She asked it the way you’d ask someone about insulin if they had type 2 diabetes.
That question lands differently when it comes from someone you’ve known for five years. Not from a TikTok influencer or a celebrity’s publicist. Not from an article designed to get clicks. From a physician who actually knows your medical history.
What the Numbers Actually Show (And What They Don’t)
Here’s what I learned in that appointment, and what I’ve learned since: GLP-1 receptor agonist prescriptions have skyrocketed by over 400 percent between 2022 and 2025. That’s not hyperbole. That’s not a trend piece exaggeration. Those are real prescriptions in real hands. One in eight American adults reports having taken a GLP-1 medication at some point, according to the KFF GLP-1 medication tracking poll. The global market for these drugs exceeded 25 billion dollars in 2025. We are not talking about a niche treatment anymore.
The clinical data is legitimately impressive. A landmark trial published in the New England Journal of Medicine obesity research showed tirzepatide producing an average weight loss of 22.5 percent of body weight over 72 weeks in adults with obesity. That’s not “lose a few pounds by summer” territory. That’s substantial, measurable, life-altering weight loss for many people. The American Medical Association updated its obesity treatment guidelines in 2025 to officially list GLP-1 medications as a first-line treatment option alongside lifestyle modifications. Not as a last resort. Not as something you consider after everything else fails. As a legitimate first option.
But here’s where I’m going to be unpopular: these numbers don’t mean what everyone wants them to mean. The fact that something is effective doesn’t make it simple. The fact that something is mainstream doesn’t mean it’s right for you. And the fact that a medication is now considered first-line treatment doesn’t mean you should take it. I needed to sit with that distinction before I could have any actual conversation with my doctor about whether this was for me.
The Part Nobody Talks About as Honestly
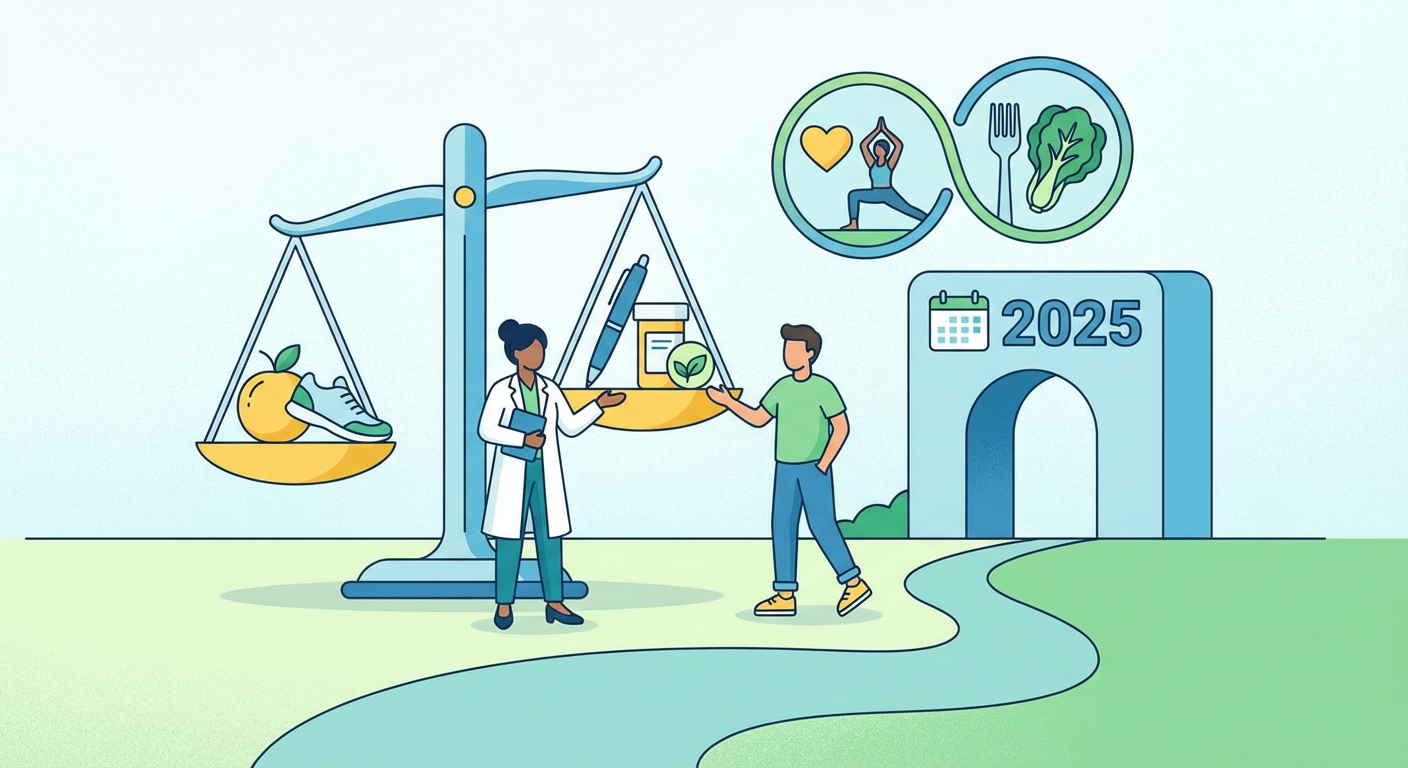
When I asked my doctor directly — “So should I start this?” — she didn’t answer the question I asked. She answered the question I should have asked: “What are you trying to accomplish, and what are you willing to accept to get there?”
She pulled up my blood work. My metabolic markers are fine. My blood pressure is fine. My A1C is fine. I’m overweight, sure. I carry about 40 extra pounds that I’d genuinely like to be rid of. But I’m not diabetic. I’m not pre-diabetic. I’m not metabolically broken. I’m just someone who eats too much and moves too little, and for whom that combination has resulted in a body that doesn’t look the way I want it to look. That’s real. That’s valid. But according to my doctor, that’s not the same as needing pharmaceutical intervention.
She also asked me about adherence and side effects. These drugs work by making you feel full faster and less interested in food. That sounds ideal until you’re dry-heaving at your desk because the medication is still working at 2 p.m. and you haven’t eaten anything because nothing sounds appealing. It sounds ideal until you’re calculating whether you have access to a bathroom at a business meeting. It sounds ideal until you realize you have to take these medications indefinitely, because most people regain the weight when they stop.
The affordability barrier is real. Forty-three percent of people who’ve taken GLP-1 medications cited cost as the reason they couldn’t continue. We’re talking about drugs that can run $1,300 per month without insurance. The pharmaceutical companies are thriving. The people who can afford these drugs are thriving. Everyone else is left making choices based on what their insurance will cover and what they can actually pay out of pocket.
What I Actually Decided, and Why I’m Still Uncertain
I’m not taking GLP-1 medication. Not right now. Not yet, anyway. My doctor said I didn’t need it, and I believed her. She also said that if I decide in the future that my relationship with food is such that medication would genuinely help me build better habits, or if my metabolic markers shift, then we’d revisit the conversation. That door is open. I’m not pretending it doesn’t exist.
But I’m also not going back to the “just eat less and move more” script that hasn’t actually worked for me for the past decade. I’m doing something different now. I’m working with a nutritionist. I’m addressing the emotional eating component that my doctor gently pointed out I’ve been ignoring. I’m being honest about what I’m actually doing with food versus what I think I’m doing. It’s slower. It’s harder. It requires confronting uncomfortable things about my own choices.
Here’s my unpopular opinion, and I mean it fully: GLP-1 drugs are probably genuinely helpful for some people. The data supports that. But they’ve also become a shortcut that lets people with money and access avoid doing the harder work of understanding their relationship with food and their bodies. And for those of us without that level of access or affordability, they’ve become another marker of inequality in healthcare. These drugs didn’t invent those dynamics. They just made them a lot more visible.
The Thing I Actually Want You to Consider
If your doctor brings this up, don’t reflexively say yes or no. Ask the harder questions. Ask whether you actually need medication or whether you need something else entirely. Ask what success looks like beyond the number on the scale. Ask about the side effects that the highlight reel doesn’t include. Ask about adherence and cost and what happens when you stop. And be honest about whether you’re considering this because it’s medically indicated or because you’re tired of being uncomfortable in your body and want the discomfort to stop faster.
Both of those are legitimate reasons, by the way. I’m not judging either path. I’m just saying the path matters, and it deserves more thought than a trending medication deserves.
I’m genuinely curious what your conversations with your own doctors have looked like. Have you asked about these medications? Did you start them? Are you considering it? I’d rather hear the messy, uncertain versions of those stories than the polished ones where everyone has clarity and perfect outcomes.